Osteoporosis, a disease which occurs more frequently in women, is characterized by low bone mass and micro-architectural deterioration of bone tissue and is the most common chronic metabolic bone disease. Annually contributing to 8.9 million fractures worldwide. Osteoporosis is associated with considerable morbidity and mortality. The prevalence of osteoporosis increases with age, and in parallel, there is an elevation in the rate of incident fragility fractures. This article explores the origins of bone and examines the physiological mechanisms involved in bone homeostasis relevant to the management and treatment of osteoporosis.
Bone is a specialized and multifunctional connective tissue with both an organic and inorganic component. The organic bone matrix (osteoid) is comprised of collagenous proteins, the predominant being type I collagen, as well as a broad range of non-collagenous proteins, including glycosaminoglycans, glycoproteins, and some serum-derived proteins. The numerous non-collagenous proteins regulate aspects of bone metabolism, including deposition, mineralization, and turnover. The inorganic component predominantly consists of calcium and phosphorus in the form of hydroxyapatite and provides mechanical rigidity to the bone, and contributes to 50–70% of the overall total bone mass.
Of the two main types of bone in the adult skeleton, cortical bone accounts for approximately 80% of the mass, and trabecular, the remaining 20%. Cortical bone is dense, has a low turnover rate of around 3% per year, and maintains the mechanical strength and integrity of the bone. In contrast, trabecular bone, found at the ends of long bones and the spinal vertebrae, has a turnover rate of approximately 26% per year, a lower mineral content, and is more metabolically active and responsive to hormonal stimuli. For example, estrogen deficiency after menopause. Trabecular bone undergoes remodeling more than cortical bone; the clinical relevance is that fragility fractures typically occur in trabecular bone.
The cellular components of bone are composed of three cell types: osteocytes, osteoblasts, and osteoclasts. Osteocytes are found in the lacunae, the small spaces within the bone matrix, and their role is to monitor and regulate mineral content. Osteoblasts, the bone-forming cells, are responsible for producing the bone matrix and initiating its mineralization. Osteoclasts are the bone-resorbing cells. Osteoclasts are large, multinucleated cells that break down (resorb) bone tissue. They are essential for bone remodeling, calcium homeostasis, and removing old or damaged bone.
All three subtypes are important for bone growth and remodeling throughout life. Bone remodeling allows repair of micro-damage, maintaining skeletal structure as well as serum calcium and phosphate homeostasis, and involves a careful equilibrium between the action of osteoclasts, the builders of bone, tightly coupled with that of osteoblasts the resorbers of bone.
Osteoporosis is metabolic bone disease that, on a cellular level result from osteoclastic bone resorption not being compensated by osteoblastic bone formation. Bone loss is an inevitable consequence of ageing. Conditions which hinder an individual’s ability to maximize peak adult bone mass, increase the probability of developing osteoporosis and elevate fracture risk later in life. Primary osteoporosis can be categorized into age-related or post-menopausal. Women have an increased risk of primary osteoporosis, insofar as they reach a lower peak bone mineral density in comparison to men. This risk is further increased by the post- menopausal decline in estrogen.
Bone loss in women is most evident in the trabecular bone as it is more metabolically active and sensitive to the trophic effects of estrogen which has a significant role in preventing bone resorption by inhibiting osteoclasts. A steeper decline in bone mass begins between 65 and 69 years in women.
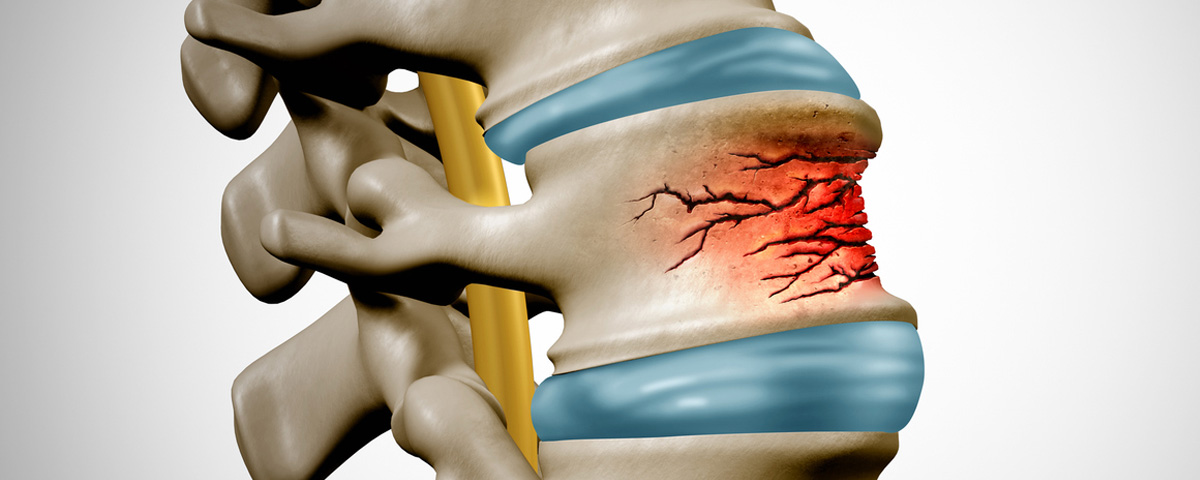
The femoral neck of the hip bone is made up of 25 50% and the vertebrae contain 75 t0 95% trabecular bone. For this reason, spine and hip fractures are the hallmark complications of trabecular bone loss in osteoporosis.
There are various pharmacological options for osteoporosis treatment that aim to reduce the risk of fractures. These include:
- Calcium and vitamin D
- Antiresorptive therapy—Bisphosphonates, Deno
- Hormonal treatment—Selective estrogen receptor modulators, Testosterone, Parathyroid hormone analogues.
- Novel therapies—Romosozumab, Dickkopf-1 (Dkk1)
In clinical practice physicians recommend bisphosphonates and denosumab. For those intolerant or who are unable to have bone sparing agents, calcium and vitamin D should be offered to maintain bone health.